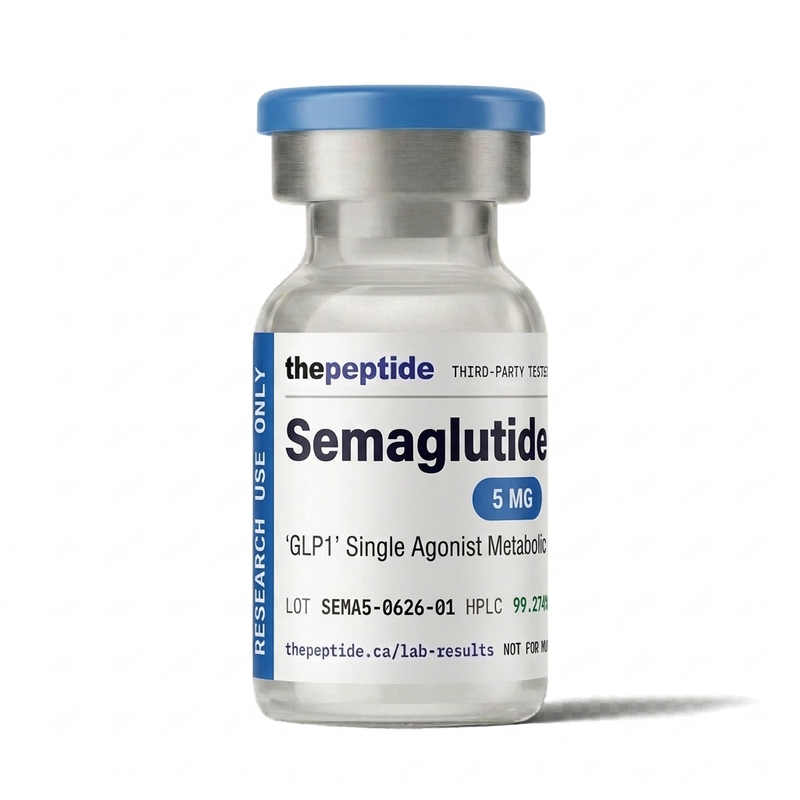
Semaglutide 5mg
GLP-1 Receptor Agonist
✓ Third-party tested — Janoshik report #101805
Assayed by Janoshik Analytical, report #101805, analysis conducted January 2026: 99.247% purity by HPLC, measured peptide content 6.05 mg against a 5 mg nominal fill.
This lot is Janoshik-only. Testides (Toronto) confirmation is pending and no Testides certificate exists for it. Four lots on this site currently hold a Testides certificate; Semaglutide 5mg is not one of them. We say so rather than let an unqualified word like "verified" imply two laboratories where there is one.
Semaglutide is a 31-residue analogue of human glucagon-like peptide-1 carrying two amino-acid substitutions and a C18 fatty diacid on Lys26, supplied here as 5 mg of lyophilised powder for laboratory research.
The interesting thing about semaglutide is not what it does at the receptor — native GLP-1 does that — but what had to be engineered so it could keep doing it. Endogenous GLP-1 has a circulating half-life of roughly one to two minutes. It is cleaved by dipeptidyl peptidase-4 at the His⁷-Ala⁸ bond within seconds of secretion, and what survives DPP-4 is cleared renally almost as fast. Semaglutide is the result of solving both problems at once, and each modification maps onto one of them.
There are exactly three changes from the GLP-1(7-37) backbone. Ala⁸ is replaced by α-aminoisobutyric acid (Aib), a quaternary, non-proteinogenic residue whose gem-dimethyl substitution sterically blocks the DPP-4 cleavage site. Lys³⁴ is replaced by arginine — not for pharmacology, but so that the acylation chemistry has only one lysine to find, making Lys²⁶ the sole and unambiguous attachment point. And Lys²⁶ carries a C18 octadecanedioic acid — a fatty diacid, not a monoacid — tethered through a γ-glutamic acid residue followed by two oligoethylene-glycol (OEG/AEEA) spacer units. The free distal carboxylate on that diacid and the length of the hydrophilic spacer together tune albumin affinity: bound to albumin, the molecule is too large to filter at the glomerulus and is shielded from proteolysis, and it is released slowly enough to maintain receptor occupancy for days. Lau and colleagues, who published the discovery programme, measured the resulting plasma half-life at 46.1 hours in mini-pigs after intravenous administration, and the Canadian product monograph for the licensed drug gives roughly one week in humans.
That trade is visible in the binding data and is worth stating because vendor copy usually inverts it. Semaglutide is less potent at the GLP-1 receptor than liraglutide — Lau reported an affinity of 0.38 ± 0.06 nM, about threefold weaker — and it is nonetheless far more effective in vivo, because duration of exposure, not peak affinity, is the limiting variable. Anyone using this vial as a reference agonist in a short in-vitro assay is measuring the property semaglutide was allowed to give up, not the one it was designed for.
The 5 mg vial is the entry size. At $44.99 it works out to $9.00 per nominal milligram, against $7.00/mg for the 10 mg vial — a 22% premium for the smaller format. On measured content the gap narrows a little, since this lot assayed at 6.05 mg rather than 5.00 ($7.44 per measured milligram), but the direction does not change. The case for the 5 mg vial is not price per milligram. It is that a smaller fill is reconstituted, aliquoted and consumed in fewer handling cycles, which matters for a molecule whose stability liabilities are handling-driven rather than intrinsic.
Semaglutide has an unusually deep human evidence base for a compound sold as a research reagent — the STEP and SUSTAIN programmes plus the SELECT cardiovascular outcome trial, tens of thousands of randomised participants — and that depth cuts both ways. It means the pharmacology is well characterised. It also means the failures, the withdrawal data and the adverse-event signals are documented in detail rather than absent, and we publish those next to the positive findings below. This vial is supplied strictly as a laboratory reagent. We give no dosing, route, schedule or administration guidance of any kind; the clinical data exist because licensed products were developed from the same molecule under regulatory oversight, not because anything on this page is a medicine.
For laboratory and research use only. Not for human consumption, veterinary use, or therapeutic application. Not approved by Health Canada. We do not provide preparation, dilution or administration guidance for any compound we sell.
Key specifications
- CAS: 910463-68-2
- Molecular weight: 4,113.58 g/mol
- Class: GLP-1 receptor agonist
- Purity: 99.247% (HPLC)
Specifications
| Compound | Semaglutide, lyophilised powder, 5 mg |
|---|---|
| Synonyms / development code | NN9535; NNC 0113-0217. Licensed product brands: Ozempic, Wegovy, Rybelsus |
| Compound class | Acylated GLP-1 receptor agonist; lipidated incretin mimetic |
| CAS number | 910463-68-2 |
| Molecular formula | C₁₈₇H₂₉₁N₄₅O₅₉ |
| Molecular weight | 4113.6 Da (Health Canada product monograph); 4113.64 g/mol average |
| Sequence (one-letter, Aib as X) | HXEGTFTSDVSSYLEGQAAK*EFIAWLVRGRG (* = acylated Lys) |
| Sequence (three-letter) | His-Aib-Glu-Gly-Thr-Phe-Thr-Ser-Asp-Val-Ser-Ser-Tyr-Leu-Glu-Gly-Gln-Ala-Ala-Lys(C18-diacid-γGlu-OEG-OEG)-Glu-Phe-Ile-Ala-Trp-Leu-Val-Arg-Gly-Arg-Gly |
| Peptide length | 31 residues; 94% sequence homology to human GLP-1; no disulfide bonds; free C-terminal acid |
| Modifications vs GLP-1(7-37) | Ala⁸ → Aib (DPP-4 resistance); Lys³⁴ → Arg (directs acylation); Lys²⁶ acylated with octadecanedioic (C18) diacid via γGlu + 2 × OEG |
| Vial contents | 5 mg lyophilised semaglutide, white to off-white, sealed vial |
| Current lot / report | Janoshik report #101805, analysis January 2026 |
| Verified purity | 99.247% |
| Measured content | 6.05 mg per vial (5 mg label) |
| Test method | HPLC purity and quantitative content determination |
| Testing laboratory | Janoshik Analytical, independent third party. Testides (Toronto) confirmation pending — no Testides certificate on this lot |
| Storage | Lyophilised: −20 °C long-term, 2–8 °C short-term; sealed, desiccated, protected from light |
| Research applications | GLP-1R binding and cAMP functional assays; β-arrestin recruitment and receptor-internalisation work; albumin-binding and plasma-protein-displacement studies; DPP-4 and plasma-stability comparisons against native GLP-1; lipidation structure–activity work; islet and enteroendocrine culture; LC-MS/MS and RP-HPLC method development and reference standard |
| Related compounds | Semaglutide 10mg · Tirzepatide 10mg · Retatrutide 10mg · Bacteriostatic water 3ml |
| Ships from | British Columbia, Canada — free tracked shipping Canada-wide, dispatched within 48 hours |
| Intended use | Laboratory research only — in vitro and preclinical. Not a drug; not for human or veterinary use |
Lab Results
- Sealed vial: −20°C, 24+ months.
- Protect from light and heat.
- Keep in original packaging until use in the laboratory.
How should lyophilised semaglutide be stored and handled?
Bench handling only. No dosing, route, schedule or administration guidance is given or implied anywhere on this page.
Lyophilised material. −20 °C is the working standard for long-term holding, 2–8 °C for short-term, sealed and desiccated and protected from light. Equilibrate the vial to room temperature before opening: peptides are hygroscopic and atmospheric moisture condenses onto cold powder, which is the most common way a dry peptide picks up water it cannot then lose.
Two liabilities are specific to this molecule and neither is obvious. First, the C18 acyl chain makes semaglutide a surfactant. It is amphiphilic by design, so it adsorbs to hydrophobic surfaces and concentrates at air–liquid interfaces — meaning low-concentration solutions lose material to polypropylene tube walls and to foam, and shaking or vortexing drives interfacial denaturation and aggregation far more readily than for an unlipidated peptide of similar size. Add diluent slowly down the vial wall and swirl or roll; never shake. Second, lipidated GLP-1 analogues are known to self-associate into oligomers in a concentration- and pH-dependent way, so behaviour is not linear across the working range and a stock prepared at one concentration is not simply a scaled version of one prepared at another.
Chemical degradation routes. There is no methionine and no cysteine in the sequence, so the two classic pathways — thioether oxidation and disulfide scrambling — do not apply. What remains is aspartate isomerisation and asparagine-free backbone hydrolysis at acidic pH, and cleavage of the amide bond joining the acyl chain to Lys²⁶ under strongly basic conditions, which would yield a des-acyl species with normal receptor potency and a completely different half-life. If a stability-indicating method is being developed, des-acyl semaglutide is the impurity worth resolving.
Reconstitution and aliquoting. Conventional laboratory diluents are sterile water or an aqueous buffer; bacteriostatic water where a multi-use aliquot is wanted. Prepare single-use aliquots before freezing so a working stock is never repeatedly thawed, and do not re-freeze reconstituted material. Commonly quoted figures for reconstituted stability — typically a few weeks at 2–8 °C — come from supplier technical monographs rather than published forced-degradation work on this molecule, and we present none as established. The licensed pharmaceutical products carry their own in-use periods, but those belong to formulated solutions with buffer, tonicity agent and preservative, and do not transfer to an unformulated peptide.
The material tolerates ambient temperature for the duration of domestic transit as a dry lyophilisate, which is why it ships without a cold chain. Move it to −20 °C on arrival.
How fast do you ship, and is delivery free across Canada?
Shipping is free and tracked, Canada-wide, on every order, with no minimum spend. Orders are dispatched within 48 hours, Monday to Friday, from our facility in British Columbia. Because the vial is already in Canada there is no international leg, no customs clearance and no brokerage on a domestic order.
Vials ship sealed and packed dry with protective padding, with the lot identifier on the label so it can be matched against the published report. A tracking number is issued at dispatch. Current transit estimates by province are on our shipping page.
What is your refund policy if a vial arrives damaged?
Report transit damage or non-delivery to info@thepeptide.ca within 48 hours of the expected delivery date, with your order number and photographs of the outer packaging and the vial where applicable. Confirmed damage and confirmed non-delivery are resolved by replacement or refund.
Sealed, unopened vials in original condition are exchangeable within 14 days of delivery. There are no refunds or exchanges on product that has been opened, punctured, reconstituted or otherwise prepared: once a seal is broken we cannot verify temperature or light exposure, and a reagent of unknown handling history is not one we will put back into circulation.
Governing terms: refund policy.
What is modified relative to human GLP-1, and why does each change matter?
Three changes, each with a distinct job. Health Canada's product monograph describes the molecule as having 94% sequence homology to human GLP-1, which is the arithmetic of two substitutions in 31 residues.
1 · Ala⁸ → Aib — proteolytic protection
Dipeptidyl peptidase-4 removes the N-terminal dipeptide of GLP-1 at the His⁷-Ala⁸ bond. α-Aminoisobutyric acid is a quaternary residue: both α-hydrogens of alanine are replaced by methyl groups, and the resulting steric bulk at the scissile position obstructs the protease. This is the modification responsible for enzymatic stability, and it is why the N-terminus — which is also the receptor-activation domain — survives long enough to matter.
2 · Lys³⁴ → Arg — synthetic regiocontrol
GLP-1 has two lysines. Acylation chemistry targeting an ε-amino group cannot distinguish them, so a molecule with two lysines yields a mixture of regioisomers. Substituting arginine at position 34 preserves the positive charge and leaves exactly one acylation site. This is a manufacturing decision, not a pharmacological one, and pages that describe it as "enhancing receptor binding" have invented a rationale.
3 · Lys²⁶ acylation — the half-life
A C18 diacid (octadecanedioic acid) attached through γ-glutamic acid and two OEG spacer units. Two details are load-bearing. The diacid leaves a free distal carboxylate, which moderates albumin affinity so the peptide is reversibly, not irreversibly, bound. The OEG units are hydrophilic and set the distance between peptide and lipid, keeping the acyl chain available to albumin without forcing the peptide backbone into the binding groove. Health Canada's monograph attributes the protracted action to albumin binding reducing renal clearance plus increased stability towards DPP-4, "resulting in a long plasma half-life of approximately one week."
At the receptor itself semaglutide is a conventional agonist at GLP-1R, a class-B1 GPCR coupling through Gs to adenylyl cyclase and cAMP. Nothing about the modifications was intended to change signalling character, and the affinity data confirm the price paid: 0.38 ± 0.06 nM, roughly threefold weaker than liraglutide (Lau 2015). Duration, not potency, is the designed property.
Is semaglutide authorised in Canada, and what changed in 2026?
Yes — three authorised products, and 2026 was the year the Canadian market changed shape. None of this makes the vial on this page an authorised drug; it is an unapproved research reagent, and the distinction is the whole point of the section.
Ozempic (semaglutide injection, type 2 diabetes) — Novo Nordisk Canada, DIN 02471469, first marketed 22 February 2018, status Marketed.
Rybelsus (oral semaglutide tablets) — Health Canada approval 9 April 2020, in Canadian pharmacies from 27 April 2020, later extended to cardiovascular risk reduction in type 2 diabetes.
Wegovy (semaglutide 2.4 mg, chronic weight management) — Health Canada approval announced 25 November 2021; Canadian availability followed later. The current monograph also carries an indication for reduction of non-fatal myocardial infarction risk, and an indication in non-cirrhotic MASH with moderate-to-advanced fibrosis that is authorised with conditions pending confirmatory trial results.
The 2026 change: Canada became the first G7 country with generic semaglutide, because of a missed fee. Novo Nordisk's Canadian composition patent, CA 2,601,784 ("Acylated GLP-1 compounds"), lapsed after a maintenance payment of roughly CAD $250 went unpaid in 2019; the last payment on record was received 23 October 2018. With the supplementary term it would otherwise have run to 20 March 2028. Health Canada approved Dr. Reddy's generic semaglutide on 28 April 2026 and Apotex on 1 May 2026, and stated it was reviewing further generic submissions. Health Canada's own announcement noted that generics in Canada are commonly 45–90% cheaper than the brand.
Why that belongs on a research-peptide page: the single largest driver of grey-market GLP-1 demand has always been price and supply of the licensed product. A Canadian generic changes that calculation in Canada specifically, and it is the sort of jurisdictional fact that vendor pages written for a US audience get wrong by omission.
Is semaglutide prohibited in sport under the WADA Code?
No. It is not on the Prohibited List. It is on the Monitoring Programme, which is a different document with different consequences. Most vendor pages in this category assert or imply a ban. That assertion is wrong, and the error is worth correcting plainly.
WADA added semaglutide to its Monitoring Programme in 2024 and has funded analytical method development for detecting GLP-1 receptor agonists in blood and dried blood spots. Monitoring exists precisely so that WADA can observe patterns of use without sanctions attaching — a substance on the Monitoring Programme is not prohibited, and a finding does not constitute an anti-doping rule violation.
That status was reaffirmed recently rather than left to inference. On 10 September 2026 WADA's Executive Committee confirmed that GLP-1 receptor agonists would not be added to the 2027 Prohibited List, keeping them on the Monitoring Programme instead. WADA's senior director for science and medicine, Professor Olivier Rabin, paired that with a caution about unsupervised use — a caution, not a prohibition.
Two honest qualifications. Monitoring status is reviewed annually and can change; "not prohibited in 2026" is not a permanent finding. And the S0 Non-Approved Substances clause catches substances with no approval from any governmental health authority for human therapeutic use — semaglutide holds authorisations from Health Canada, FDA and EMA, so S0 does not reach the molecule, though it may reach an unapproved preparation of it. Any athlete in a tested sport should obtain a written determination from their national anti-doping organisation rather than rely on any vendor's reading, including ours.
What does the semaglutide evidence not support?
It does not support any claim of durable effect after withdrawal. This is the single most consistently omitted finding in the category and it has its own block below.
It does not support a mortality benefit in the general population. SELECT enrolled 17,604 people with established cardiovascular disease, overweight or obesity, and no diabetes, and measured major adverse cardiovascular events against placebo. Whatever it found holds only inside a narrowly defined high-risk population. It is not evidence about anyone outside it, and the trial was not designed to answer questions about primary prevention.
It does not support tolerability claims. In SELECT, 16.6% of semaglutide participants discontinued because of adverse events versus 8.2% on placebo — double, mostly gastrointestinal, in a trial where participants had strong reason to persist. Any page describing the tolerability profile as mild is contradicted by the largest dataset available.
It does not support treating weight change as fat-specific. STEP 1 measured mean body-weight change against placebo over 68 weeks in 1,961 participants without diabetes. Body weight is not body composition, and the trial's primary endpoint was weight. Claims about lean-mass preservation require body-composition endpoints that these trials largely did not prespecify.
It does not support the MASH indication as settled. The Canadian Wegovy monograph carries that indication authorised with conditions, which is Health Canada's mechanism for approving on promising but incomplete evidence pending confirmatory trials. That is a weaker status than a standard authorisation and should be described as such.
And a limit on what we can tell you: essentially all of this human evidence comes from the licensed pharmaceutical product, manufactured to a defined specification with a defined excipient package. None of it is evidence about an unformulated research peptide, and we do not present it as such.
What happens when semaglutide is withdrawn?
The effect reverses, and this was measured rather than inferred. The STEP 1 trial extension followed 327 participants for a further 52 weeks after both semaglutide and placebo were stopped at week 68.
Week 0 → 68, on treatment: mean body-weight change measured against placebo.
Week 68 → 120, off treatment: semaglutide participants regained much of the weight lost; placebo participants regained comparatively little.
Roughly two-thirds of the loss returned by week 120.
The authors also report that cardiometabolic improvements seen from week 0 to week 68 "reverted towards baseline at week 120 for most variables." The effect on those markers is a function of ongoing exposure, not a durable physiological reset.
STEP 4 is the mirror image and makes the same point from the other direction: participants who continued semaglutide after a 20-week run-in kept losing weight, while those randomised to placebo regained. Mechanistically this is unsurprising — a receptor agonist acting on an intact, feedback-regulated appetite and gastric-emptying system leaves little trace once occupancy falls. Any protocol asking about persistence needs a withdrawal arm; the compound will not answer the question on its own.
How reliable are the pancreatitis, gallbladder and gastroparesis signals?
They differ sharply in quality, and collapsing them into one "GLP-1 risks" paragraph — which most pages do — destroys the distinction that matters.
Gallbladder disease: the strongest signal, and dose- and indication-dependent. He et al. pooled 76 randomised trials and 103,371 participants: gallbladder or biliary disease RR 1.37 (95% CI 1.23–1.52); cholelithiasis 1.27 (1.10–1.47); cholecystitis 1.36 (1.14–1.62). The subgroup structure is the informative part. In the 13 trials using GLP-1 agonists for weight loss, RR was 2.29 (1.64–3.18), against 1.27 (1.14–1.45) in the 63 diabetes and other trials. Higher doses gave RR 1.56 (1.36–1.78); lower doses 0.99 (0.73–1.33). Longer duration 1.40 (1.26–1.56); shorter 0.79 (0.48–1.31). A clean exposure–response gradient across three independent axes is what a real signal looks like. It is also partly confounded by rapid weight loss itself, which is an established gallstone risk factor independent of any drug.
Pancreatitis, bowel obstruction and gastroparesis: widely cited, much weaker than the citations suggest. The source is Sodhi et al., a retrospective claims-database cohort. Read the numbers rather than the headline: there were 613 semaglutide users and 4,144 liraglutide users against 654 bupropion-naltrexone comparators, and the adjusted hazard ratio for pancreatitis was 9.09 with a 95% CI of 1.25 to 66. A confidence interval spanning a 53-fold range is a statement about how few events were observed. Bowel obstruction was 4.22 (1.02–17.40); gastroparesis 3.67 (1.15–11.90); biliary disease 1.50 (0.89–2.53), not significant. The authors themselves flag the absence of dose and duration data, ICD coding misclassification, and a study population mostly with diabetes — which independently causes gastroparesis.
A subsequent reanalysis, published in Alimentary Pharmacology & Therapeutics in 2025 under the title "Some Risks of Gastrointestinal Adverse Events Associated With Glucagon-Like Peptide-1 Receptor Agonists Are Likely Explained by BMI," concluded that part of the apparent excess is attributable to baseline BMI rather than drug exposure. We could not retrieve that paper's full text and therefore quote none of its effect estimates; we cite it only for the direction of its conclusion.
The common events are not the interesting ones but they are the real ones. Health Canada's own review summary for Wegovy records gastrointestinal disorders in 73% of participants, headache in 16% and fatigue in 11%, with a 16-week dose-escalation schedule designed specifically to mitigate the GI burden. Frequent, mostly transient, and the dominant reason people stop.
Why is compounded semaglutide everywhere, and what is its legal status?
This is the question a Canadian buyer actually has, almost no vendor answers it honestly, and the answer differs by country. We are not lawyers and none of this is legal advice.
United States — the window opened on a shortage and has closed. Large-scale compounding of semaglutide was lawful only while FDA listed the drug as in shortage, which permits compounders to make copies under sections 503A and 503B. FDA declared the semaglutide injection shortage resolved on 21 February 2025, with enforcement discretion ending 22 April 2025 for 503A pharmacies and 22 May 2025 for 503B outsourcing facilities. Tirzepatide had gone first: removed from the shortage list 2 October 2024, with deadlines of 18 February and 19 March 2025. On 30 April 2026 FDA went further and proposed to exclude semaglutide, tirzepatide and liraglutide from the 503B bulks list entirely, stating it "did not identify a clinical need for outsourcing facilities to compound" them from bulk substances, with comments open to 29 June 2026.
Canada — there was never a window. Canada has no shortage-triggered compounding exemption of the American kind. Health Canada's position, circulated to pharmacy regulators in June 2025, is that these activities constitute manufacturing rather than compounding, because they generally use unauthorised active pharmaceutical ingredients and duplicate an available authorised product without an unmet therapeutic need. Provincial regulators including the Alberta College of Pharmacy have stated plainly that unauthorised compounding of semaglutide-containing products is not permitted.
Why this reaches a research-reagent page. Health Canada's public advisory of 9 April 2026 on injectable peptides bought online named 14 compounds — BPC-157, CJC-1295, DSIP, Epitalon, GHK-Cu, HCG, Ipamorelin, KPV, Melanotan I and II, MOTS-C, NAD+, SS-31, TB-500 and Retatrutide. Semaglutide was not among them. That absence is a fact, not a shield: the advisory's operative sentence is that research-use-only labelling "does not make these products legal or exempt from regulatory requirements." On 11 June 2026 the Superior Court of Québec granted Health Canada a permanent injunction against a Québec online peptide retailer, barring manufacture, testing, distribution and sale of unauthorised injectable peptides and advertising through sites reachable from Canadian IP addresses. Neither action named semaglutide; both establish reasoning that does not depend on the compound.
We publish this knowing it cuts against our own interest, because the alternative is pretending a disclaimer is a legal shield when two regulators have now said it is not. So the research framing has to be real rather than decorative: we supply a reagent, publish no dosing or administration guidance, and make no human-use claims. Whether a particular purchase, import or use is lawful in your circumstances is a question for a Canadian regulatory lawyer, not for a product page.
Should I choose the 5 mg vial or the 10 mg vial?
Same compound, same supplier, different economics and different handling profile. The honest summary is that the 10 mg vial is cheaper per milligram and the 5 mg vial is easier to consume without compromise.
Semaglutide 5mg — $44.99
$9.00 per nominal mg; $7.44 per measured mg on this lot's 6.05 mg content. Suits method development, single-experiment reference standards, small-scale binding or cAMP work, and any protocol where the reconstituted stock would otherwise sit through more freeze–thaw cycles than you are willing to justify in a methods section.
Semaglutide 10mg — $69.99
$7.00 per nominal mg; $6.13 per measured mg on that lot's 11.42 mg content. A 22% lower unit cost. Suits replicate work, dose–response series, extended timecourse experiments and anything where a single lot across all conditions removes inter-lot variability as a confounder. Details on the Semaglutide 10mg page, which also covers the brand-name and manufacturing-route questions this page does not.
The argument that actually decides it is not price. One lot across an entire experiment is worth more than a small saving. If the work spans conditions that must be comparable, buy the size that covers all of them from one vial — a lot change mid-series introduces a variable you cannot control for retrospectively. If the work is exploratory and the next experiment may use something else entirely, the smaller vial wastes less.
Both vials are supplied as a single sealed fill with no excipient, and each is characterised by its own lot report, so the purity and content figures are not transferable between them. Check the number on the label against the published report for that lot specifically.
What was measured on this lot, and what was not?
Two numbers, from one laboratory, on one lot. Janoshik Analytical, report #101805, analysis conducted January 2026: purity 99.247%, measured peptide content 6.05 mg against a 5 mg nominal fill. Report numbers are published for every lot on our lab results page.
Those two figures answer different questions and conflating them is the commonest error in reading a certificate of analysis. Purity is the proportion of chromatographic peak area attributable to the target peptide — how much of the peptide present is the intended sequence rather than truncations, deletions, des-acyl species or degradation products. It says nothing about how much is in the vial. Content is the absolute mass determination, the figure that governs any quantitative solution, and the one most often omitted. A vial can be 99% pure and underfilled, or correctly filled and 90% pure. You need both, from the same lot, with the lot matching the label. Full walkthrough: how to read a peptide COA.
Measured content here exceeds the nominal fill by about 21%, which is ordinary in lyophilised fills and is not a defect — but a calculation assuming exactly 5.00 mg will be wrong by that margin, which is more than enough to move a dose–response curve.
What this report does not cover. It is an HPLC purity and quantitative content assay. It carries no mass-spectrometry identity confirmation, no endotoxin or bioburden testing, no residual-solvent or heavy-metal analysis, no aggregation assessment, and no counter-ion or salt-content determination.
Testides (Toronto) confirmation is pending on this lot. Four lots on this site hold a Testides certificate — Tirzepatide 10mg, Retatrutide 10mg, BPC-157 10mg and the Wolverine Blend. Semaglutide 5mg is not one of them, and we do not describe it as if it were.
One point nobody in this category raises. The salt form matters and is not stated on an HPLC report. Synthetic peptides are commonly isolated as acetate or trifluoroacetate salts, and total vial mass is not peptide mass. Quantitative content determination measures the peptide, which is the right quantity — but if you are reconciling a gravimetric weight against a content figure, the counter-ion accounts for part of the difference. We do not print a salt form for this lot because it was not assayed, and we will not state one we have not measured.
Which published studies on semaglutide matter most, and how were they designed?
Every citation below was checked against a MEDLINE-derived record or a publisher page. Design and size are stated because they determine what each result can support.
1. Lau J, Bloch P, Schäffer L, et al. Discovery of the Once-Weekly Glucagon-Like Peptide-1 (GLP-1) Analogue Semaglutide. J Med Chem. 2015;58(18):7370–7380. PMID 26308095. — The discovery paper. In vitro and animal. Source for the Aib⁸/Arg³⁴ substitutions, Lys²⁶ derivatisation, GLP-1R affinity 0.38 ± 0.06 nM and the 46.1 h mini-pig intravenous half-life.
2. Marso SP, et al. Semaglutide and Cardiovascular Outcomes in Patients with Type 2 Diabetes. N Engl J Med. 2016;375(19):1834–1844. PMID 27633186. — SUSTAIN-6. Randomised, double-blind, placebo-controlled cardiovascular safety trial in type 2 diabetes; the first outcome evidence for the molecule.
3. Wilding JPH, et al. Once-Weekly Semaglutide in Adults with Overweight or Obesity. N Engl J Med. 2021;384(11):989–1002. PMID 33567185. — STEP 1. Randomised, double-blind, placebo-controlled, n = 1,961, 68 weeks, measuring mean body-weight change against placebo.
4. Davies M, Færch L, Jeppesen OK, et al. Semaglutide 2·4 mg once a week in adults with overweight or obesity, and type 2 diabetes (STEP 2). Lancet. 2021;397(10278):971–984. PMID 33667417. — Randomised, double-blind, double-dummy, placebo-controlled phase 3. The type 2 diabetes population, where weight effects are consistently smaller than in STEP 1.
5. Rubino D, et al. Effect of Continued Weekly Subcutaneous Semaglutide vs Placebo on Weight Loss Maintenance: The STEP 4 Randomized Clinical Trial. JAMA. 2021;325(14):1414–1425. PMID 33755728. — Randomised withdrawal design after a 20-week run-in; the continuation-versus-withdrawal comparison.
6. Wilding JPH, Batterham RL, Davies M, et al. Weight regain and cardiometabolic effects after withdrawal of semaglutide: The STEP 1 trial extension. Diabetes Obes Metab. 2022. doi:10.1111/dom.14725. PMID 35441470. — The citable source on discontinuation. n = 327 followed to week 120, measuring weight regained off treatment; cardiometabolic variables reverted towards baseline. We could not confirm the final volume and page range against a primary record and therefore give the DOI and PMID instead.
7. He L, et al. Association of Glucagon-Like Peptide-1 Receptor Agonist Use With Risk of Gallbladder and Biliary Diseases: A Systematic Review and Meta-analysis of Randomized Clinical Trials. JAMA Intern Med. 2022. PMID 35344001. — 76 randomised trials, 103,371 participants. Overall RR 1.37 (1.23–1.52), with the dose, duration and indication gradients given above. Volume and page range not independently confirmed; year and PMID are.
8. Sodhi M, Rezaeianzadeh R, Kezouh A, Etminan M. Risk of Gastrointestinal Adverse Events Associated With Glucagon-Like Peptide-1 Receptor Agonists for Weight Loss. JAMA. 2023. PMID 37796527. — Retrospective claims-database cohort, not randomised. 613 semaglutide users. Pancreatitis aHR 9.09 (95% CI 1.25–66). Cited here for the width of its intervals as much as for its point estimates.
9. Lincoff AM, Brown-Frandsen K, Colhoun HM, et al. Semaglutide and Cardiovascular Outcomes in Obesity without Diabetes. N Engl J Med. 2023;389(24):2221–2232. PMID 37952131. — SELECT. Randomised, double-blind, placebo-controlled, n = 17,604, mean follow-up 40 months, measuring a primary MACE composite against placebo. Discontinuation for adverse events 16.6% versus 8.2%.
YOU MAY ALSO LIKE
SHOP ALL



Frequently Bought Together
Laboratory supplies commonly ordered alongside research compounds.

Bacteriostatic Water 10mL — Sterile Multi-Use Laboratory Water with 0.9% Benzyl Alcohol
Sterile Preserved Laboratory Water
STARTING AT ▸ $22.00